Deep Cleaning Cost Factors: Quadrant Billing & Clinical Drivers
What clinical and administrative factors determine the cost of periodontal scaling and root planing, and how does quadrant billing work?
When a dental clinician recommends periodontal scaling and root planing (often referred to as a "deep cleaning"), patients frequently encounter unfamiliar billing terms, quadrant codes, and varied out-of-pocket estimates. Understanding the clinical drivers behind periodontal therapy fees—including standardized ADA CDT coding, clinical chair time, anesthesia requirements, and post-treatment maintenance—allows patients to evaluate treatment estimates transparently.
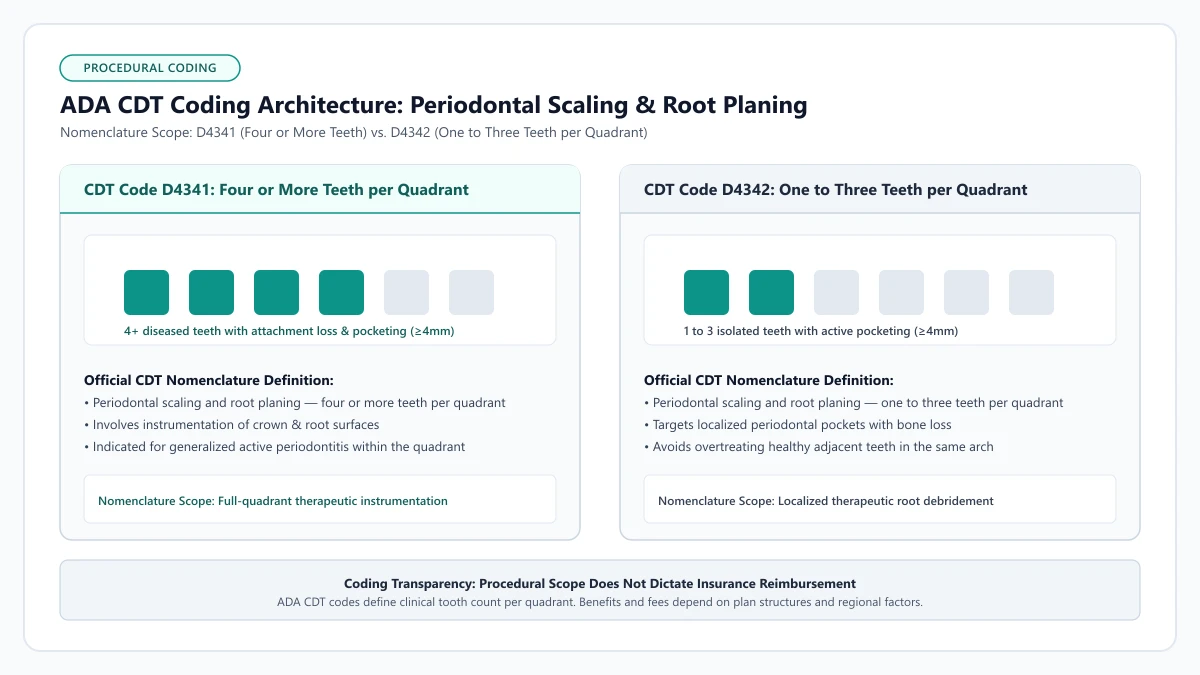
Educational illustration: ADA CDT coding definitions for periodontal scaling and root planing by tooth count per quadrant. Coding nomenclature defines procedural scope and does not establish clinical fees or insurance reimbursement.
Source: RecedingGumline.com Clinical Editorial Team (Proprietary educational diagram for RecedingGumline.com)
Key Clinical Distinctions & Diagnostic Boundaries
- Standard dental prophylaxis (CDT D0110) cleans coronal tooth surfaces in healthy mouths, whereas scaling and root planing (D4341/D4342) is a therapeutic intervention for active periodontal disease.
- ADA CDT code D4341 applies specifically to quadrants with four or more teeth exhibiting disease, whereas D4342 applies to localized quadrants with one to three affected teeth.
- Coding nomenclature and insurance benefit reimbursement are separate: payer policies, deductibles, and annual maximums determine coverage rather than the CDT code alone.
- Scaling and root planing is followed by periodic periodontal maintenance (CDT D4910), representing an ongoing clinical and financial commitment to prevent recurrent disease.
Standardized ADA CDT Procedure Coding
Dental procedural billing is organized under the American Dental Association’s Code on Dental Procedures and Nomenclature (ADA CDT). In periodontal therapy, standardized codes distinguish between extensive quadrant therapy and localized intervention.
Code D4341 is defined as "periodontal scaling and root planing — four or more teeth per quadrant." This code applies when subgingival calculus, root surface roughness, and clinical attachment loss affect four or more diseased teeth within an anatomical quadrant.
Code D4342 is defined as "periodontal scaling and root planing — one to three teeth per quadrant." This localized code represents therapy restricted to one, two, or three affected teeth within a quadrant, requiring less clinical chair time than a full-quadrant procedure.
It is important to understand that procedure coding and insurance reimbursement are distinct. A CDT code standardizes what clinical service was provided, but does not dictate the clinician’s fee or obligate third-party payers to approve coverage. Payer policies vary widely in their clinical criteria and reimbursement rates.
Clinical Considerations:
- D4341: Periodontal scaling and root planing — four or more teeth per quadrant
- D4342: Periodontal scaling and root planing — one to three teeth per quadrant
- CDT codes provide administrative nomenclature rather than establishing clinical necessity or fees
- Insurance reimbursement depends on individual carrier contracts, plan exclusions, and deductibles
Clinical Chair Time, Instrumentation & Anesthesia
The primary determinant of scaling and root planing costs is clinical chair time. Unlike a routine preventive cleaning, thorough scaling and root planing typically requires 45 to 90 minutes per appointment, often scheduled over two to four separate appointments depending on disease severity.
During the procedure, dental clinicians meticulously debride subgingival root surfaces, removing hardened calculus deposits and microbial biofilm from pocket concavities and root furcations using ultrasonic instruments and delicate hand curettes.
Because subgingival debridement reaches below the gumline into sensitive root areas, local anesthesia is frequently administered to ensure patient comfort. Depending on the dental practice, local anesthetic delivery may be included within the comprehensive quadrant fee or listed as a separate administrative item.
Clinical Considerations:
- Thorough root instrumentation requires substantial clinician time compared to preventive cleanings
- Procedures are frequently divided into multiple visits to ensure comfort and thoroughness
- Ultrasonic scalers and specialized hand curettes are utilized to debride deep root surfaces
- Local anesthesia policies vary by practice regarding inclusion in the base quadrant fee
Diagnostic Prerequisites & Adjunctive Considerations
A comprehensive periodontal treatment plan incorporates essential diagnostic examinations that precede active therapy. These prerequisites ensure that periodontal therapy is clinically substantiated before instrumentation begins.
Diagnostic prerequisites include detailed periodontal charting (CDT D0180) measuring probing depths at six points per tooth, and diagnostic periapical radiographs (CDT D0210) to evaluate interdental alveolar bone margins (Tonetti et al., 2018).
Clinicians may also discuss therapeutic adjuncts, such as localized subgingival antimicrobials (CDT D4381) or antimicrobial irrigation. Patients should discuss with their provider whether proposed adjunctive therapies are clinically indicated for their specific pocket depths or represent optional adjuncts.
Clinical Considerations:
- Standardized periodontal probing charting is required to verify pocket depths and attachment loss
- Diagnostic radiographs provide necessary visualization of alveolar bone architecture
- Subgingival antimicrobial adjuncts may be discussed for specific refractory or deep pockets
- Patients should ask for an itemized breakdown of recommended diagnostic and adjunctive services
The Long-Term Periodontal Maintenance Commitment
An important clinical and financial aspect of periodontal therapy is that scaling and root planing is not a permanent, one-time treatment. Following therapy, tissues undergo a healing interval of 4 to 8 weeks, after which a re-evaluation probing examination is conducted to assess tissue response.
Following active scaling and root planing, patients transition from standard prophylaxis into ongoing periodontal maintenance (CDT D4910). Periodontal maintenance appointments are typically recommended every 3 to 4 months to monitor pocket depths and disrupt re-emerging subgingival biofilms.
Dental benefit plan coverage for periodontal maintenance varies significantly by policy. Many dental plans limit reimbursement to two maintenance visits per benefit year or apply separate deductibles, making ongoing maintenance a recurring personal health investment in preserving natural teeth.
Clinical Considerations:
- Post-treatment re-evaluation assesses tissue response and pocket depth reduction
- Patients transition into ongoing periodontal maintenance (CDT D4910) rather than preventive cleanings
- Maintenance visits are typically scheduled at 3- to 4-month intervals based on individual risk
- Insurance coverage rules for maintenance visits vary widely across different benefit plans
Clinical Reality Check
A dental procedure code is an administrative naming tool, not an automatic guarantee of insurance reimbursement or a universal fee schedule. Clinical fees vary based on geographic location, provider practice setting, and defect complexity, and dental benefit plans enforce independent clinical policies regarding which procedures they reimburse.
Questions to Ask Your Periodontist or Dentist
- How many quadrants or localized sites in my mouth require scaling and root planing based on my periodontal probing chart?
- Does my treatment estimate use code D4341 (four or more teeth) or D4342 (one to three teeth) for each recommended quadrant?
- Are local anesthesia, diagnostic radiographs, and antimicrobial adjuncts included in the quadrant estimate or billed separately?
- What will my ongoing periodontal maintenance recall schedule look like once active treatment is completed?
Unsure What Your Gum Changes Mean?
Take our free, evidence-based Gum Recession Assessment — approximately 3 minutes. Identify potential risk factors, evaluate symptoms, and receive personalized discussion questions for your dentist or periodontist.
Non-diagnostic educational triage. Private, secure, completed in your browser.
Related Educational Topics
Clinical Evidence & Claim Traceability (3 Mapped Assertions)
Scientific Literature & Clinical Guidelines
2sources · Hide ▲
- American Dental Association (2026).
"Code on Dental Procedures and Nomenclature (CDT)." American Dental Association.Coding Standard Official Publication
Clinical relevance: Standardized dental procedure nomenclature maintained and updated annually by the American Dental Association (ADA, currently referencing CDT 2026/2027) for administrative classification and billing (including codes D4273, D4275, D4277, D4341, D4910). The site references CDT procedure numbers for high-level educational and administrative context and does not reproduce proprietary CDT descriptors or substantial CDT text. Commercial use/licensing requirements should be reviewed separately with the ADA or qualified counsel. Procedure codes facilitate administrative reporting and do not dictate clinical necessity or insurance benefit coverage.
- Tonetti MS, Greenwell H, Kornman KS (2018).
"Staging and grading of periodontitis: Framework and proposal of a new classification and case definition." Journal of Clinical Periodontology.
Clinical relevance: Consensus framework establishing the multidimensional staging (severity and extent of periodontal tissue breakdown) and grading (biological rate of disease progression, incorporating smoking and diabetes as grade modifiers) for periodontitis. It addresses periodontitis diagnosis and staging, not the classification of localized gingival recession defects.
Important Medical Notice
The contents of RecedingGumline.com, including text, graphics, self-assessment calculators, and other materials, are intended solely for educational and informational purposes. This content is not intended to replace professional dental examination, diagnosis, or treatment. Always seek the advice of a qualified dentist, periodontist, or other licensed oral healthcare provider with any questions you may have regarding a medical or dental condition. Never disregard professional medical advice or delay seeking it because of something you read on this website.