Gum Grafting vs. Monitoring: Clinical Decision Framework
How do periodontists determine whether receding gums warrant surgical grafting or can be safely monitored over time?
When gingival recession is detected, clinicians evaluate whether to recommend soft-tissue grafting or proceed with structured clinical monitoring. This clinical judgment is not determined by appearance alone or an arbitrary measurement cutoff, but relies on comprehensive parameters including tissue phenotype, historical progression across recall visits, patient symptoms, plaque control, and interproximal bone stability.
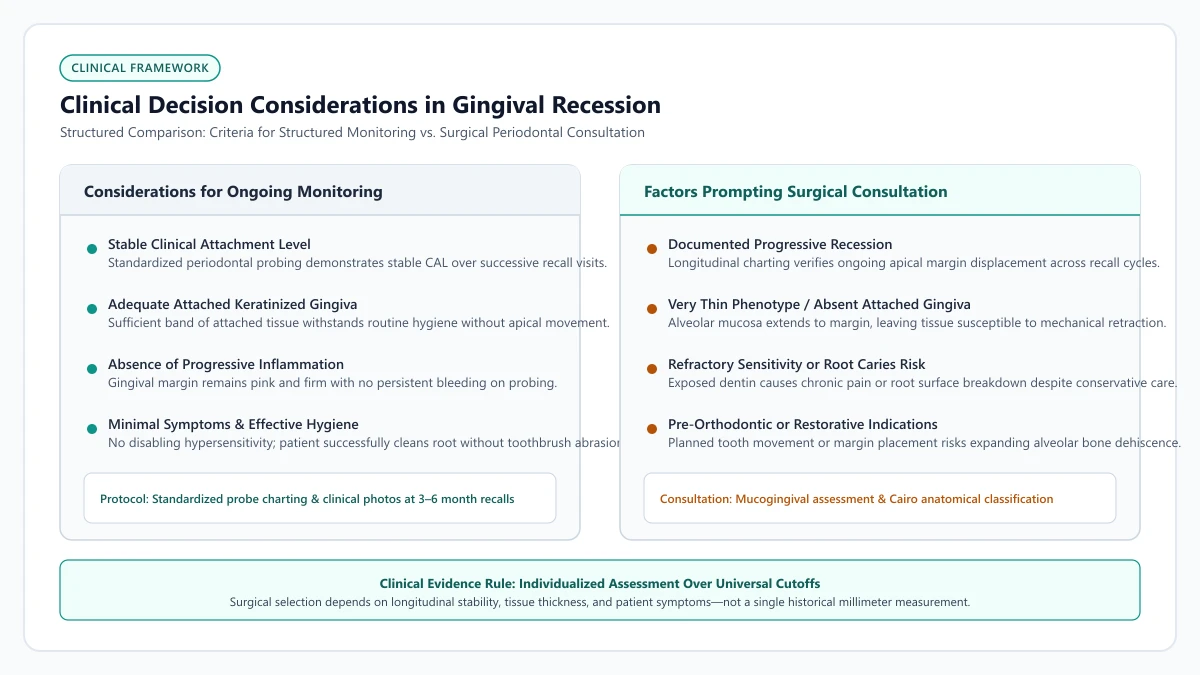
Educational diagram: Decision considerations in gingival recession management. Treatment decisions depend on longitudinal stability, tissue phenotype, and individual patient symptoms rather than a single isolated measurement.
Source: RecedingGumline.com Clinical Editorial Team (Proprietary educational diagram for RecedingGumline.com)
Key Clinical Distinctions & Diagnostic Boundaries
- Recession depth alone does not mandate surgery; progressive attachment loss documented across successive recall visits is a primary clinical consideration.
- Keratinized tissue width below historical reference points (such as 2 mm) is evaluated alongside tissue phenotype, patient symptoms, and hygiene access, not as an automatic surgical rule.
- Cairo RT1 defects (intact interdental bone) offer high predictability for complete root coverage, whereas RT2 and RT3 defects have reduced coverage potential; however, classification predicts outcomes rather than determining surgical necessity.
- Clinical monitoring requires standardized periodontal charting and photographic records at regular 3- to 6-month intervals, not passive unmeasured observation.
When Structured Clinical Monitoring Is Appropriate
Not every area of gum recession requires surgical intervention. When an exposed root surface is asymptomatic, easily cleaned, and surrounded by stable tissue, structured clinical monitoring is frequently the recommended protocol.
Active monitoring is a disciplined clinical regimen rather than passive observation. During routine 3- to 6-month recall visits, your clinician records standardized periodontal measurements, including probing depths, clinical attachment level (CAL), and keratinized tissue width.
If comparative charting confirms that the gingival margin has remained stable across consecutive recall cycles without bleeding on probing, hypersensitivity, or functional impairment, surgical intervention offers limited therapeutic necessity unless root coverage is specifically desired for aesthetic reasons.
Clinical Considerations:
- Stable clinical attachment level confirmed across 12 or more months of standardized charting
- Absence of persistent marginal inflammation or bleeding on probing during recall evaluations
- Patient demonstrates effective, non-traumatic plaque control without ongoing mechanical abrasion
- Site remains clinically manageable and free of progressive non-carious cervical lesions
Clinical Factors in Surgical Grafting Decisions
Periodontal literature identifies several clinical scenarios where surgical soft-tissue grafting may be discussed. A primary clinical consideration is documented apical progression of recession across consecutive recall examinations.
Historical periodontal literature (such as early work by Lang and Löe) discussed 2 millimeters of keratinized tissue as a desirable threshold for maintaining gingival health. However, contemporary periodontal consensus emphasizes that a specific width measurement does not serve as an automatic universal rule. While movable alveolar mucosa bordering the margin can make plaque removal challenging in some individuals, many sites with narrow keratinized bands remain healthy when gentle, meticulous hygiene is maintained.
Surgical evaluation also considers severe root hypersensitivity that fails to respond to conservative desensitizing dentifrices or topical agents, aesthetic concerns in high smile lines, and planned orthodontic movements that may shift a tooth through a thin alveolar cortical plate.
Clinical Considerations:
- Documented apical migration of the gingival margin over consecutive clinical evaluations
- Narrow or absent attached tissue accompanied by persistent inflammation or difficult hygiene access
- Persistent root hypersensitivity compromising comfortable oral hygiene or daily mastication
- Pre-orthodontic evaluation in patients presenting with thin gingival phenotypes in planned movement paths
Defect Classification & Root Coverage Predictability
The anatomical predictability of root coverage grafting is largely governed by interproximal bone and soft-tissue height, as categorized by the Cairo et al. (2011) classification system. Cairo Recession Type 1 (RT1) defects feature intact interdental attachment with no bone loss between teeth.
In RT1 defects, subepithelial connective tissue grafting combined with coronally advanced flaps demonstrates high predictability for achieving complete root coverage in clinical trials (Chambrone et al., 2018). The intact interproximal papillae and vascular bed provide critical nourishment to the repositioned tissue during wound healing.
In Cairo RT2 defects, where interproximal attachment loss is present but less than or equal to buccal recession, complete root coverage is less predictable because the interdental bone crest has receded. In RT3 defects, interproximal attachment loss exceeds buccal loss, meaning root coverage cannot be reliably predicted. In these presentations, classification serves as an anatomical prognostic tool rather than an independent decision rule for whether surgery should occur.
Clinical Considerations:
- Cairo RT1: Intact interdental bone; complete root coverage is anatomically predictable if surgery is indicated
- Cairo RT2: Interproximal loss present; partial root coverage may be achieved depending on interdental height
- Cairo RT3: Severe interproximal attachment loss; complete coverage cannot be biologically predicted
- Classification frameworks describe outcome predictability rather than mandating surgical intervention
Risks & Considerations in Longitudinal Monitoring
When progressive recession occurs in an individual with a thin periodontal phenotype, ongoing observation without addressing contributing factors carries clinical considerations. As marginal tissue recedes, thin facial alveolar bone may undergo concurrent remodeling.
If recession progresses unchecked and begins to affect interproximal bone, an RT1 defect can transition toward an RT2 presentation. Once interdental bone support is lost, the anatomical predictability of achieving complete root coverage is biologically reduced.
A collaborative discussion with your periodontist should examine longitudinal charting records, familial risk factors, brushing mechanics, and personal functional needs before deciding between surgical management and continued clinical observation.
Clinical Considerations:
- Unchecked apical migration in thin phenotypes may involve progressive loss of the thin facial bone plate
- Transition from Cairo RT1 to RT2 reduces future root coverage predictability if surgery is later required
- Longitudinal decision-making balances measured stability against individual aesthetic and functional goals
- Regular standardized clinical charting remains essential to verify that observation remains safe
Clinical Reality Check
A narrow zone of keratinized tissue or stable, asymptomatic recession does not automatically necessitate surgical correction. When an individual maintains meticulous, non-traumatic oral hygiene and clinical charting verifies dimensional stability over consecutive years, structured observation avoids unnecessary surgical intervention.
Questions to Ask Your Periodontist or Dentist
- Has my recession depth or clinical attachment loss changed when comparing my current measurements to previous charting records?
- What is my current width of attached keratinized tissue, and does it show signs of inflammation or mechanical instability during brushing?
- Based on my interproximal bone levels (Cairo classification), what degree of root coverage would be biologically realistic if surgery were pursued?
- Are there non-surgical strategies, such as modifying my brushing technique or applying desensitizing agents, that we should evaluate before considering surgery?
Unsure What Your Gum Changes Mean?
Take our free, evidence-based Gum Recession Assessment — approximately 3 minutes. Identify potential risk factors, evaluate symptoms, and receive personalized discussion questions for your dentist or periodontist.
Non-diagnostic educational triage. Private, secure, completed in your browser.
Related Educational Topics
Clinical Evidence & Claim Traceability (3 Mapped Assertions)
Scientific Literature & Clinical Guidelines
3sources · Hide ▲
- Cairo F, Nieri M, Cincinelli S, Mervelt J, Pagliaro U (2011).
"The interproximal clinical attachment level to classify gingival recessions and predict root coverage outcomes: an explorative and reliability study." Journal of Clinical Periodontology.
Clinical relevance: Exploratory and reliability study establishing the Cairo classification based on interdental clinical attachment level (CAL): RT1 (no interproximal attachment loss; complete root coverage is clinically predictable), RT2 (interproximal attachment loss <= buccal loss; partial coverage predictable), and RT3 (interproximal loss exceeds buccal recession; complete coverage not predictable).
- Chambrone L, Salinas Ortega MA, Sukekava F, Rotundo R, Kalemaj Z, Buti J, Pini Prato GP (2018).
"Root coverage procedures for treating localised and multiple recession-type defects." Cochrane Database of Systematic Reviews.
Clinical relevance: Cochrane systematic review evaluating root-coverage procedures for localized and multiple recession-type defects. While subepithelial connective tissue grafts (SCTG) combined with coronally advanced flaps demonstrated higher rates of complete root coverage and keratinized tissue gain compared to flap advancement alone, evidence quality varied across outcomes and clinical decisions must balance donor site morbidity and patient-reported outcomes.
- Zucchelli G, Mounssif I (2015).
"Periodontal plastic surgery." Periodontology 2000.
Clinical relevance: Peer-reviewed review of periodontal plastic surgery modalities, detailing flap design, coronally advanced flaps, autogenous connective tissue grafting, tunneling techniques, and anatomical factors governing aesthetic and functional root coverage.
Important Medical Notice
The contents of RecedingGumline.com, including text, graphics, self-assessment calculators, and other materials, are intended solely for educational and informational purposes. This content is not intended to replace professional dental examination, diagnosis, or treatment. Always seek the advice of a qualified dentist, periodontist, or other licensed oral healthcare provider with any questions you may have regarding a medical or dental condition. Never disregard professional medical advice or delay seeking it because of something you read on this website.