Pinhole Technique vs. Connective Tissue Graft: Objective Comparison
How do the Pinhole Surgical Technique and connective tissue grafting compare in terms of root coverage, tissue thickness, and clinical evidence?
When surgical intervention is evaluated for gingival recession, patients often encounter two distinct approaches: the Pinhole Surgical Technique (PST) and autogenous subepithelial connective tissue grafting (SCTG). While patient discussions frequently focus on surgical invasiveness and recovery time, peer-reviewed periodontal literature evaluates these techniques based on clinical root coverage, keratinized tissue augmentation, donor-site considerations, and trial documentation.
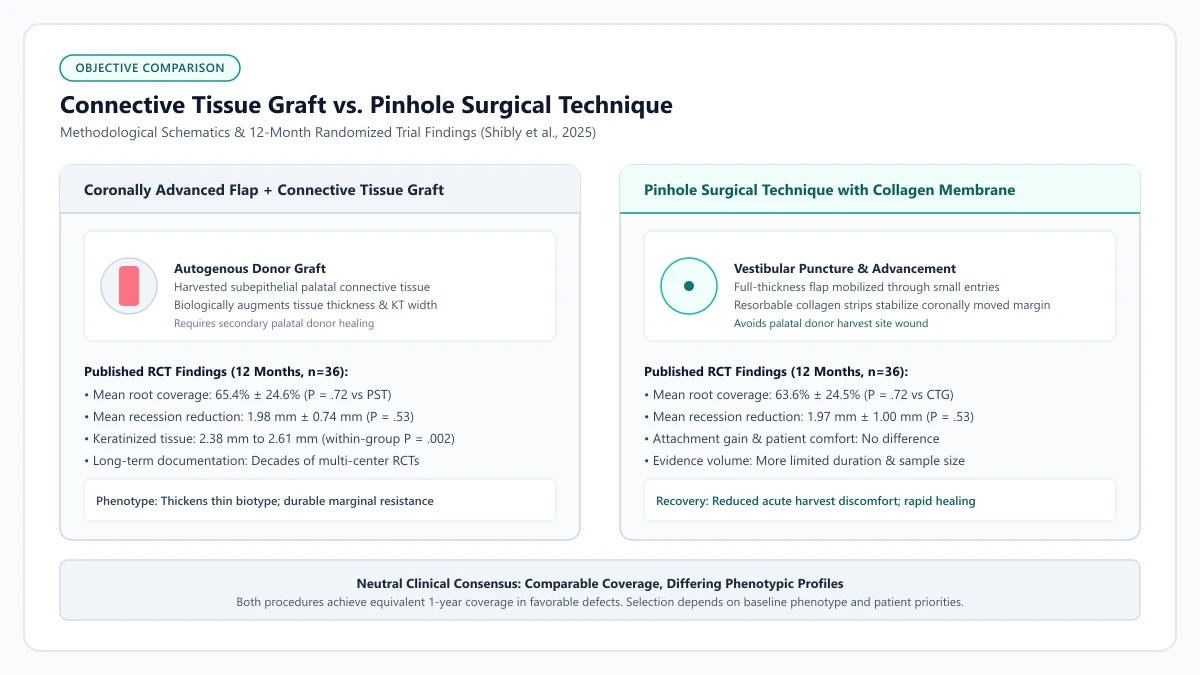
Educational illustration: Conceptual comparison of autogenous connective tissue grafting and the pinhole surgical technique. Individual anatomical factors and baseline keratinized tissue dimensions guide clinical procedure selection.
Source: RecedingGumline.com Clinical Editorial Team (Proprietary educational diagram for RecedingGumline.com)
Key Clinical Distinctions & Diagnostic Boundaries
- Connective tissue grafting incorporates an autogenous donor graft that biologically augments gingival thickness and keratinized tissue width.
- The Pinhole Surgical Technique elevates and coronally advances existing local mucosal tissue, stabilizing it with resorbable collagen strips without harvesting palatal tissue.
- A 2025 split-mouth randomized trial found similar 1-year recession reduction (1.97 mm vs 1.98 mm) and root coverage (63.6% vs 65.4%), with the CAF + CTG group demonstrating a statistically significant within-group keratinized-tissue-width increase over baseline.
- Connective tissue grafting possesses extensive multi-decade systematic review evidence, whereas randomized clinical trial data directly evaluating pinhole techniques remains more limited in volume and duration.
Surgical Mechanisms & Biological Differences
Subepithelial connective tissue grafting (SCTG) involves harvesting a layer of autogenous collagenous connective tissue from the patient’s palate. This graft is secured over the denuded root surface beneath an advanced flap or microsurgical tunnel, supplying viable fibroblasts and an extracellular matrix that revascularizes from adjacent periodontal tissues.
The Pinhole Surgical Technique (PST) utilizes small vestibular puncture incisions in the movable mucosa. Specialized instruments are inserted through these entry points to gently release and elevate a full-thickness flap, allowing the clinician to stretch the existing marginal tissue coronally over exposed roots. Resorbable collagen membrane strips are then positioned through the punctures to stabilize the repositioned tissue during initial healing without palatal harvesting.
The fundamental biological difference centers on graft material: autogenous connective tissue grafting introduces new structural tissue volume derived from the patient, whereas the pinhole technique mobilizes and repositions existing local tissues with temporary membrane support.
Clinical Considerations:
- SCTG transfers living autogenous connective tissue from the hard palate to augment tissue volume
- PST mobilizes existing local gingival tissues coronally through small puncture entries
- PST utilizes resorbable collagen strips to stabilize elevated margins during early healing
- SCTG incorporates an autogenous collagen matrix that integrates directly into local microvasculature
Comparative Clinical Evidence & Trial Findings
Subepithelial connective tissue grafting combined with coronally advanced flaps has been evaluated in hundreds of clinical investigations, with Cochrane systematic reviews (Chambrone et al., 2018) documenting high rates of complete root coverage and durable long-term stability across diverse defect types.
Until recently, direct comparative randomized trials evaluating the pinhole technique alongside connective tissue grafting were limited. In 2025, Shibly and colleagues published a 12-month split-mouth randomized clinical trial involving 36 patients with bilateral Miller Class I and II recession defects, directly comparing the Pinhole Surgical Technique with collagen membrane against coronally advanced flap with connective tissue graft.
At 1-year follow-up, the trial observed similar outcomes between groups for mean recession reduction (1.97 mm ± 1.00 mm for pinhole vs 1.98 mm ± 0.74 mm for CAF + CTG, between-group P = .53), mean root coverage (63.6% ± 24.5% vs 65.4% ± 24.6%, between-group P = .72), clinical attachment-level gain, and patient-centered outcomes. The CAF + CTG group showed a statistically significant increase in keratinized-tissue width over its own baseline measurement (from 2.38 mm ± 1.5 mm to 2.61 mm ± 1.07 mm, within-group P = .002). The published abstract does not establish from those figures alone that this was a statistically significant between-treatment difference.
The investigators observed comparable 12-month root coverage and recession reduction between the two surgical approaches in this trial cohort, while connective tissue grafting remains supported by a broader multi-decade volume of systematic reviews across diverse defect configurations.
Clinical Considerations:
- Cochrane systematic review evidence documents long-term stability for connective tissue grafting across diverse defects
- A 2025 split-mouth RCT (Shibly et al.) observed similar 12-month recession reduction and root coverage between PST and CTG
- The CAF + CTG group showed a statistically significant increase in keratinized-tissue width over its own baseline measurement
- Trial findings must be interpreted within study parameters: 36 subjects, 12-month follow-up, and specific defect criteria
Phenotype Modification & Long-Term Considerations
A primary therapeutic goal in periodontal plastic surgery is often phenotype modification—enhancing thin marginal tissue into a thicker, more resilient tissue band that can withstand daily mechanical stresses.
Autogenous connective tissue grafting consistently increases both the apicocoronal width of keratinized tissue and the faciolingual thickness of the gingival margin (Zucchelli & Mounssif, 2015). This increased thickness has been correlated with reduced rates of recession recurrence over extended follow-up periods.
Because the pinhole procedure primarily repositions existing tissue, its capacity to convert a very thin phenotype into a dense, thick band appears more limited based on available trial data. In sites presenting with paper-thin tissue or an absence of attached gingiva, periodontists often consider autogenous grafting to establish lasting structural reinforcement.
Clinical Considerations:
- Connective tissue grafting provides proven biological thickening of thin periodontal phenotypes
- Gaining keratinized tissue width supports long-term marginal resistance against mechanical trauma
- Pinhole techniques rely primarily on advancing existing tissue, with collagen membranes providing temporary scaffolding
- Anatomical defect characteristics and interproximal bone levels (Cairo classification) influence both approaches
Surgical Morbidity, Recovery & Clinical Selection
A notable aspect of the pinhole approach is the avoidance of a palatal donor site. Patients typically experience mild localized swelling and minimal discomfort during the immediate postoperative window, generally resuming routine light activities within 24 to 48 hours.
In connective tissue grafting, harvesting donor tissue from the palate introduces a secondary surgical site. Modern microsurgical methods—such as single-incision access, mucosal tunneling, and custom protective stents—have substantially reduced palatal discomfort. Nevertheless, the palatal donor site requires 10 to 14 days of dedicated care and dietary adjustments.
Clinical selection between these modalities is individualized. Factors include the number of adjacent affected teeth, baseline keratinized tissue dimensions, aesthetic expectations, patient tolerance for a palatal donor site, and the clinical experience of the treating periodontist.
Clinical Considerations:
- Pinhole technique avoids a secondary palatal harvest wound, typically resulting in less acute early discomfort
- Modern palatal harvesting techniques reduce donor-site morbidity during connective tissue grafting
- The absence of a palatal wound does not independently establish clinical suitability for all defect types
- Comprehensive periodontal examination determines which surgical philosophy aligns with specific patient needs
Clinical Reality Check
Choosing between the Pinhole Surgical Technique and autogenous connective tissue grafting depends heavily on baseline tissue phenotype, the presence of attached keratinized gingiva, defect extent, and patient priorities regarding donor-site recovery. Minimizing harvest morbidity does not automatically make one procedure universally preferable for all defect configurations.
Questions to Ask Your Periodontist or Dentist
- Is my recession defect better characterized as localized or generalized, and which technique provides predictable outcomes for my specific defect type?
- Do I have sufficient baseline keratinized tissue, or does my site require autogenous donor tissue to increase tissue thickness?
- What are the documented long-term stability records for each technique in your specific clinical practice?
- What should I anticipate regarding postoperative comfort, healing timeline, and activity restrictions for each procedure?
Unsure What Your Gum Changes Mean?
Take our free, evidence-based Gum Recession Assessment — approximately 3 minutes. Identify potential risk factors, evaluate symptoms, and receive personalized discussion questions for your dentist or periodontist.
Non-diagnostic educational triage. Private, secure, completed in your browser.
Related Educational Topics
Clinical Evidence & Claim Traceability (5 Mapped Assertions)
Scientific Literature & Clinical Guidelines
4sources · Hide ▲
- Shibly O, Chao JC, Albandar JM, Almehmadi N, Al-Sabbagh M (2025).
"Treatment of Gingival Recession Using the Pinhole Surgical Technique With Collagen Membrane Vs Coronally Advanced Flap Technique With Connective Tissue Graft: A Split-Mouth Randomized Clinical Trial." Compendium of Continuing Education in Dentistry.Peer-Reviewed Study PMID:40009192
Clinical relevance: Split-mouth randomized clinical trial of 36 subjects (72 sites) comparing pinhole surgical technique (PST) with collagen membrane to coronally advanced flap with connective tissue graft (CAF+CTG) for Miller Class I and II recession defects over 12 months. Both modalities achieved similar mean recession reduction (1.97 mm vs 1.98 mm, P = .53), mean root coverage (63.6% vs 65.4%, P = .72), clinical attachment gain, and patient-centered outcomes, with no statistically significant differences between groups. The CAF + CTG group showed a statistically significant increase in keratinized-tissue width over its own baseline measurement (from 2.38 mm to 2.61 mm, within-group P = .002); the published abstract does not establish from those figures alone that this was a statistically significant between-treatment difference.
- Chambrone L, Salinas Ortega MA, Sukekava F, Rotundo R, Kalemaj Z, Buti J, Pini Prato GP (2018).
"Root coverage procedures for treating localised and multiple recession-type defects." Cochrane Database of Systematic Reviews.
Clinical relevance: Cochrane systematic review evaluating root-coverage procedures for localized and multiple recession-type defects. While subepithelial connective tissue grafts (SCTG) combined with coronally advanced flaps demonstrated higher rates of complete root coverage and keratinized tissue gain compared to flap advancement alone, evidence quality varied across outcomes and clinical decisions must balance donor site morbidity and patient-reported outcomes.
- Zucchelli G, Mounssif I (2015).
"Periodontal plastic surgery." Periodontology 2000.
Clinical relevance: Peer-reviewed review of periodontal plastic surgery modalities, detailing flap design, coronally advanced flaps, autogenous connective tissue grafting, tunneling techniques, and anatomical factors governing aesthetic and functional root coverage.
- Cairo F, Nieri M, Cincinelli S, Mervelt J, Pagliaro U (2011).
"The interproximal clinical attachment level to classify gingival recessions and predict root coverage outcomes: an explorative and reliability study." Journal of Clinical Periodontology.
Clinical relevance: Exploratory and reliability study establishing the Cairo classification based on interdental clinical attachment level (CAL): RT1 (no interproximal attachment loss; complete root coverage is clinically predictable), RT2 (interproximal attachment loss <= buccal loss; partial coverage predictable), and RT3 (interproximal loss exceeds buccal recession; complete coverage not predictable).
Important Medical Notice
The contents of RecedingGumline.com, including text, graphics, self-assessment calculators, and other materials, are intended solely for educational and informational purposes. This content is not intended to replace professional dental examination, diagnosis, or treatment. Always seek the advice of a qualified dentist, periodontist, or other licensed oral healthcare provider with any questions you may have regarding a medical or dental condition. Never disregard professional medical advice or delay seeking it because of something you read on this website.